
Overview of Joint Injections
Osteoarthritis (OA) is a chronic, progressive joint disease that cannot currently be cured. Intra-articular (IA) therapies, or joint injections, allow treatment to be delivered directly into an affected joint. Depending on the product, the goals may include reducing pain and inflammation, improving the joint environment, and potentially decreasing reliance on systemic medications.
Joint injections have traditionally been considered later in the course of OA, particularly when systemic therapies are no longer providing adequate comfort, but that approach is changing. Some IA therapies may have a role earlier in OA management, including in dogs with mild to moderate disease. There is no single best IA therapy for every dog (or cat). Product selection should be individualized according to the joint involved, stage and characteristics of disease, treatment goals, available evidence, cost, and the dog’s overall OA management plan.
IA therapy should be considered one component of multimodal OA management rather than a replacement for weight management, appropriate exercise, physical rehabilitation, environmental modification, and other indicated pain management strategies.
How Are Joint Injections Performed?
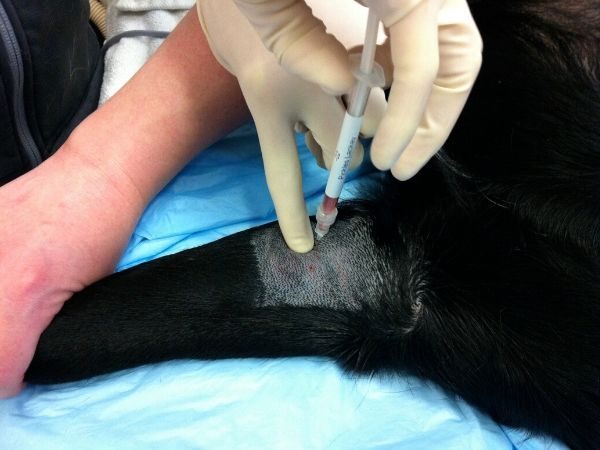
Joint injection requires appropriate training, patient sedation, and strict aseptic technique. Ultrasound guidance can be particularly helpful for joints that are more difficult to access, such as the shoulder and hip. There is a learning curve for performing joint injections, and iatrogenic cartilage damage is common, especially in small joints and when learning to perform IA injections. Some veterinarians advocate for US guidance for all injections, though this is not universally performed.
Synovial fluid can be aspirated before injection to confirm intra-articular needle placement and to reduce joint distension. Injection volume matters because overdistension of the joint can contribute to post-injection discomfort. Transient soreness may occur after IA treatment, and larger injection volumes and repeated attempts to enter the joint may increase this risk. Most dogs are rested for several days after injection, followed by a gradual return to normal activity over the next one to two weeks.
The duration of benefit varies considerably among products and individual dogs. Repeat treatment may be appropriate, and the optimal frequency for re-injection is not known and likely differs among products injected. Reinjection should be based on the dog’s clinical response and the characteristics of the product being used.
What Can Be Injected Into a Joint?
Hyaluronic Acid (HA)
Hyaluronic acid is a normal component of cartilage and synovial fluid and contributes to joint lubrication. In OA, naturally occurring HA becomes fragmented, which reduces the quality of synovial fluid and may contribute to a more inflammatory joint environment. Injected HA is intended to improve the joint environment and may influence inflammation as well as lubrication.
Canine studies have reported improvements in pain, lameness, function, and range of motion after IA HA. Benefits appear to be relatively short lived when HA is used alone, commonly diminishing by about six months. Available evidence does not clearly show an advantage to giving a series of injections rather than a single injection. Higher molecular weight products more closely resemble HA found in healthy joints and are generally preferred. HA is also frequently combined with other IA therapies, including corticosteroids and orthobiologic products.
Corticosteroids
Intra-articular corticosteroids can provide relatively rapid reduction in joint inflammation and pain and are inexpensive compared with many other injectable options. Triamcinolone is commonly used and may be less harmful to cartilage than some alternative corticosteroids.
The major limitation is concern about adverse effects on articular cartilage, particularly with repeated injections. For this reason, corticosteroids are generally used selectively rather than as a routine repeated treatment. They may be considered for dogs with advanced OA that has been refractory to other options, when rapid control of substantial noninfectious synovitis is desired, or when financial constraints limit access to other IA therapies. Corticosteroids are often combined with HA.
Platelet-Rich Plasma (PRP)
Platelet-rich plasma is prepared from blood and uses the biologic activity of platelets and their associated growth factors and signaling molecules to influence inflammation and the joint environment. PRP can be produced in the clinic using specialized centrifugation or filtration systems.
Importantly, PRP is not a single standardized product. Commercial systems can produce substantially different concentrations of platelets, leukocytes, neutrophils, and red blood cells. For intra-articular use, current evidence favors a product with increased platelet concentration, minimal red blood cell contamination, and low leukocyte and neutrophil content. Clinicians should understand the cellular composition produced by the system they use rather than assuming all PRP preparations are equivalent.
Clinical research in dogs is increasingly supportive of PRP for OA, although comparison among studies is difficult because preparation methods, injection protocols, affected joints, and outcome measures vary. Improvements in pain and lameness are commonly reported. After a single injection, benefit is often reported for approximately three to six months, while some studies using repeat injections have reported effects extending toward one year. Evidence also suggests that dogs receiving NSAIDs do not necessarily need to discontinue them solely because PRP is being administered.
Autologous Protein Solution and Autologous Conditioned Serum
Autologous protein solution (APS) and autologous conditioned serum (ACS) are blood-derived therapies designed to concentrate anti-inflammatory proteins and growth factors. APS (brand name Pro-Stride®), uses additional processing to concentrate platelets, leukocytes, and proteins including interleukin-1 receptor antagonist. ACS (brand name Orthokine® or IRAP), is produced by incubating whole blood with specialized beads before separating the serum.
Canine clinical studies of APS have demonstrated improvement in pain, lameness, and objective weight bearing compared with saline controls. Clinical effects can occur relatively quickly and may persist for several months, with some dogs experiencing benefit for six to twelve months.
Mesenchymal Stromal Cell Therapy
Mesenchymal stromal cell (MSC) therapy is often described as regenerative medicine, but that terminology can overstate what has been demonstrated clinically. There is currently no evidence that IA MSC therapy regenerates normal hyaline cartilage in dogs with naturally occurring OA. The primary therapeutic goal is modulation of the joint environment, particularly inflammation, with subsequent improvement in comfort and function.
Both adipose-derived and bone marrow-derived MSCs have been used in dogs, and there is not currently clear evidence that one autologous source is clinically superior to the other. Culture-expanded MSC preparations provide larger and more consistent cell populations but require more time. Bone marrow aspirate concentrate (BMAC) and adipose-derived stromal vascular fraction can be prepared more quickly, but contain relatively few MSCs along with multiple other cell types, cytokines, and growth factors.
Clinical studies generally support the safety of IA MSC therapy and have reported improvements in owner-assessed comfort, activity, and lameness. Until evidence demonstrates meaningful cartilage restoration in clinical patients, treatment success should be judged primarily by changes in pain, inflammation, function, and quality of life rather than claims of joint regeneration.
Radiosynoviorthesis with Tin-117m (Synovetin OA®)
Synovetin OA uses the radioisotope tin-117m to target synovial macrophages, the primary cells that contribute to synovitis and production of inflammatory cytokines. After macrophages take up the radioisotope, low-energy electron emission causes macrophage apoptosis, reducing inflammatory activity within the synovium.
Canine clinical studies have reported reductions in pain and improvements in weight bearing and function that can persist for up to a year after a single injection. The radioisotope has a short penetration range and remains within the treated joint, but its use requires specific radiation-safety procedures. In the United States, administration requires a practice with the appropriate radioactive materials license, and caregivers must follow temporary contact restrictions after treatment. Synovetin OA is FDA approved for canine elbow OA, although regulatory requirements may vary by jurisdiction.
Polyacrylamide Hydrogel (Arthramid®)
Polyacrylamide hydrogel is a newer category of IA treatment intended to alter the mechanical environment of the joint. Arthramid is a 2.5% cross-linked polyacrylamide hydrogel classified as a medical device. Rather than acting primarily as a drug, the material integrates with the synovial membrane and is intended to support synovial tissue, joint fluid quality, joint capsule elasticity, lubrication, and cushioning.
Evidence in horses suggests that 2.5% polyacrylamide hydrogel can provide sustained clinical benefit, with a slower onset than some other injectables. It has been used in canine patients, but there are no robust clinical trials supporting it’s efficacy or safety in dogs at this time.
Collagen-Elastin Hydrogel Particles (Spryng®)
Spryng is a collagen-elastin hydrogel particle product classified as a medical device. After injection, the particles are intended to assemble within the synovium and provide a scaffold that supports the mechanical properties and elasticity of the joint capsule.
Evidence for this product is currently very limited.
Summary of Products for IA use: This is an evolving area and data remain limited for most products. Clinicians should apply evidence-guided clinical reasoning with selecting a product for IA use. Recommendations may change as independent clinical data become available.
Choosing an Intra-Articular Therapy
There is no universal hierarchy of joint injections for canine OA. The evidence base, mechanism, expected onset and duration, cost, regulatory requirements, and the individual dog’s disease should all be considered. Some products have canine randomized clinical data, while others are supported primarily by studies in other species or by clinical experience. Those differences should be transparent when discussing options with caregivers.
IA therapies also do not need to be reserved for dogs with end-stage OA. Depending on the product and the patient, they may be considered across the OA spectrum. Earlier use may be particularly relevant when the goal is to influence the inflammatory joint environment while disease is less advanced. At the same time, evidence is not yet sufficient to establish a single ideal product, combination, or treatment schedule for every dog.
Key Takeaways
- Joint injections provide targeted treatment and may be appropriate at multiple stages of OA, not only as a last resort.
- There is no single best intra-articular therapy for every dog.
- PRP and other blood-derived products differ substantially in composition, so clinicians should understand the product they are preparing and injecting.
- MSC therapy may improve pain and function, but should not currently be presented as proven cartilage regeneration.
- Newer hydrogel products are promising, but the strength of canine evidence is limited.
- Good case selection, sterile technique, appropriate sedation, accurate needle placement, and realistic caregiver expectations are essential to successful IA therapy.
References
Rychel J, Fry L, Pechette A. Chapter 22: Intra-articular therapies. In: Shaw KK, Capon S, eds. Canine Osteoarthritis and Chronic Pain. Wiley; 2026.
Alves JC, Santos A, Carreira LM. A preliminary report on the combined effect of intra-articular platelet-rich plasma injections and photobiomodulation in canine osteoarthritis. Animals. 2023;13(20). doi:10.3390/ani13203247.
Aulakh KS, Lopez MJ, Hudson C, et al. Prospective clinical evaluation of intra-articular injection of Tin-117m radiosynoviorthesis agent for management of naturally occurring elbow osteoarthritis in dogs: a pilot study. Vet Med (Auckl). 2021;12:117-128. doi:10.2147/VMRR.S295309.
Carr BJ, Miller AV, Colbath AC, Peralta S, Frye CW. Literature review details and supports the application of platelet-rich plasma products in canine medicine, particularly as an orthobiologic agent for osteoarthritis. J Am Vet Med Assoc. 2024;262(S1):S8-S15. doi:10.2460/javma.23.12.0692.
Carapeba GOL, Cavaleti P, Nicacio GM, et al. Intra-articular hyaluronic acid compared to traditional conservative treatment in dogs with osteoarthritis associated with hip dysplasia. Evid Based Complement Alternat Med. 2016;2016:2076921. doi:10.1155/2016/2076921.
Franklin SP, Cook JL. Prospective trial of autologous conditioned plasma versus hyaluronan plus corticosteroid for elbow osteoarthritis in dogs. Can Vet J. 2013;54(9):881-884.
Franklin SP, Franklin AL. Randomized controlled trial comparing autologous protein solution to hyaluronic acid plus triamcinolone for treating hip osteoarthritis in dogs. Front Vet Sci. 2021;8:713768. doi:10.3389/fvets.2021.713768.
Harman R, Carlson K, Gaynor J, et al. A prospective, randomized, masked, and placebo-controlled efficacy study of intraarticular allogeneic adipose stem cells for the treatment of osteoarthritis in dogs. Front Vet Sci. 2016;3:81. doi:10.3389/fvets.2016.00081.
Kim S, Elam L, Johnson V, et al. Intra-articular injections of allogeneic mesenchymal stromal cells vs. high molecular weight hyaluronic acid in dogs with osteoarthritis: exploratory data from a double-blind, randomized, prospective clinical trial. Front Vet Sci. 2022;9:890704. doi:10.3389/fvets.2022.890704.
Maki CB, Beck A, Wallis CBC, et al. Intra-articular administration of allogeneic adipose derived MSCs reduces pain and lameness in dogs with hip osteoarthritis: a double blinded, randomized, placebo controlled pilot study. Front Vet Sci. 2020;7:570. doi:10.3389/fvets.2020.00570.
Miller AV, Carney PC, Markmann A, Frye CW. Retrospective analysis describes safety of therapeutic joint injections in dogs. J Am Vet Med Assoc. 2023;261(3):397-402. doi:10.2460/javma.22.11.0483.
Pashuck TD, Kuroki K, Cook CR, Stoker AM, Cook JL. Hyaluronic acid versus saline intra-articular injections for amelioration of chronic knee osteoarthritis: a canine model. J Orthop Res. 2016;34(10):1772-1779. doi:10.1002/jor.23191.
Wanstrath AW, Hettlich BF, Su L, et al. Evaluation of a single intra-articular injection of autologous protein solution for treatment of osteoarthritis in a canine population. Vet Surg. 2016;45(6):764-774. doi:10.1111/vsu.12512.